
Foot complications
Charcot foot: the warm, swollen foot you shouldn’t keep walking on
In a foot that has lost feeling, a minor injury can set off inflammation that weakens the bones until they break and the arch collapses. Charcot foot is rare and easily mistaken for an infection or a sprain, and the first few weeks of care decide the shape the foot ends up in.
Written by the Managing Neuropathy editorial team under the direction of Dr. Tom Biernacki, DPM, FACFAS · Clinical review pending · Last updated 13 November 2026
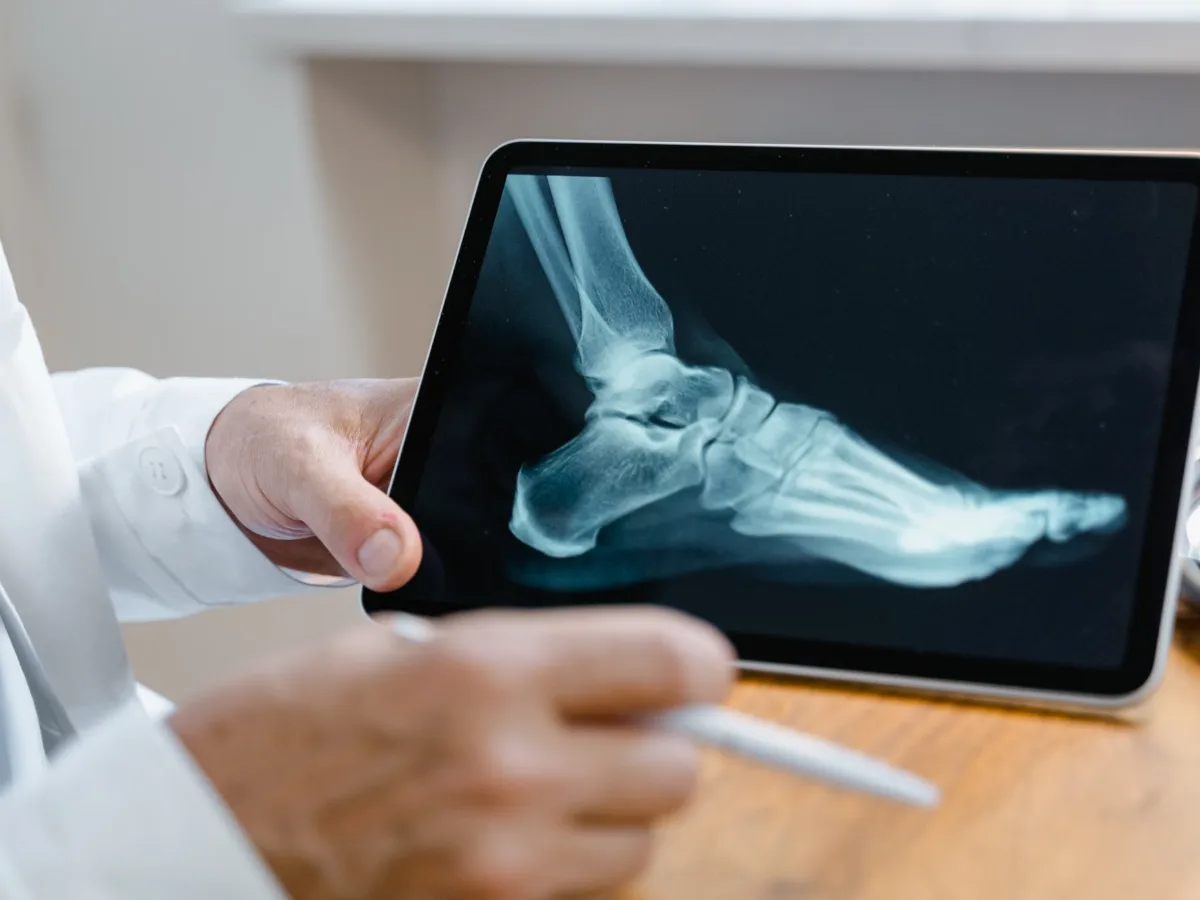
The short answer. Charcot foot (Charcot neuro-osteoarthropathy) is a complication of neuropathy, most often from diabetes, in which the bones and joints of the foot or ankle weaken, break and shift, usually after an injury too small to notice. The first sign is a foot that is warmer, more swollen and often redder than the other one, with surprisingly little pain. It is easily mistaken for cellulitis, gout, a sprain or a blood clot. Treatment is to immobilize the foot and take weight off it, ideally in a total contact cast, for several months until the inflammation settles. If you have numb feet and one foot suddenly turns warm and swollen, get it seen urgently by a foot specialist, and keep your weight off it until you are.
What happens in a Charcot foot
Charcot foot is inflammation in the bones and joints of the foot or ankle that leads to fractures, dislocations and, without treatment, a permanently changed foot. It is named after the French neurologist Jean-Martin Charcot, who described this kind of joint destruction in the 1800s in people whose nerves had been damaged by syphilis. Today diabetes is by far the most common cause.
It usually starts with an injury: a twist, a stumble, a long day on your feet, often something the person doesn’t remember. In a UK audit of 288 cases, only about a third recalled any injury in the six months before. In a foot with normal feeling, a cracked bone hurts, so you limp and rest it, and the inflammation of healing settles. In a numb foot you keep walking. Every step adds damage, the inflammation keeps going, and the inflammation itself switches on the cells that break down bone. The bones soften, crack and shift, and the joints slip out of place.
The classic result is a collapse of the middle of the foot into a “rocker-bottom” shape: the arch drops until the sole curves outward, like the bottom of a rocking chair. Bony points on the sole then take pressure they were never built to take, and that is where ulcers start. Charcot can also affect the ankle, the back of the foot and the joints of the forefoot.
Who gets it
Charcot foot needs neuropathy. An international task force convened by the American Diabetes Association and the American Podiatric Medical Association noted that no case has been reported without it. Most people who develop it are in their 50s or 60s and have had diabetes and numb feet for years. Other causes of numb feet can do it too, including alcohol-related neuropathy, leprosy, spinal cord damage and, less often, inherited neuropathies such as Charcot-Marie-Tooth disease.
It is uncommon. Studies from England, Ireland and Denmark found it in 0.04% to about 0.5% of people with diabetes. That still adds up: the International Working Group on the Diabetic Foot (IWGDF) estimates that 1.6 million people worldwide are living with it, with 160,000 new cases a year, and believes the true number is higher because it is so often missed. People who have had a kidney or pancreas transplant appear to be at higher risk, possibly because of the steroids that protect the transplant.
Having it in one foot raises the stakes for the other. In a Swiss clinic that followed 159 people for a median of about five years, 16% had both feet affected when first diagnosed, and nearly one in five of the rest developed it in the second foot, typically about a year after the first.
The early signs
- One foot is warmer than the other, often by several degrees. Clinicians compare the two feet with an infrared thermometer, and many studies have used a difference of about 2°C (4°F) as a marker, though no cut-off has been proven.
- Swelling of the foot or ankle, often with redness.
- Less pain than you would expect, or none at all, because of the neuropathy. Some people do have significant pain, so pain or the lack of it doesn’t settle anything.
- A change in shape: a flatter arch, a new bony bump on the sole or the side of the foot, or an ankle that starts to look crooked. This usually comes later, after damage has been done.
In Charcot the skin is usually intact. An open sore, a crack between the toes, pus or feeling feverish and unwell point toward infection, which can happen alongside Charcot and needs urgent care of its own.
Why it gets missed
Early Charcot looks like other things. The ADA and podiatry task force says it resembles cellulitis (a skin infection), a deep vein thrombosis (a blood clot in the leg) or acute gout, and it can be mistaken for a sprain. Early X-rays are often normal, which can be falsely reassuring. And because it doesn’t hurt much, people keep walking on it while they wait for an appointment.
That is why the IWGDF’s first recommendation is that clinicians always consider active Charcot in a person with diabetes, neuropathy and intact skin whose foot is warmer, more swollen or redder than the other one. NICE in the UK goes further: consider it even when there is no deformity and no pain. If you have neuropathy and you are being treated for “cellulitis” or a “sprain” in a hot, swollen foot that isn’t improving, ask directly whether it could be Charcot.
How it’s diagnosed
- An examination comparing the two feet for warmth, swelling and shape, plus checks of feeling and circulation. The monofilament test.
- A temperature comparison, measuring the hottest point on the affected foot against the same point on the other foot.
- X-rays of both feet, ideally taken standing, so the two sides can be compared and any collapse shows.
- An MRI if the X-rays are normal but Charcot is still suspected. It can show swelling inside the bone and small fractures while X-rays still look normal. If MRI isn’t possible, a bone scan or CT scan can help.
Blood tests can’t diagnose or rule out Charcot, the IWGDF says, though your clinician may still order them while looking for infection. The same guideline makes a point that matters more to you than any test: if Charcot is suspected, the foot should be immobilized in a knee-high device straight away, while the tests are being done. Walking on the foot for two weeks while you wait for an MRI is exactly how a deformity forms.
The stages
| Stage | What is happening | What you notice | What imaging shows |
|---|---|---|---|
| 0 (early) | Inflammation, bone bruising and small cracks | A warm, swollen, often red foot | Normal X-rays; changes on MRI |
| 1 (fragmentation) | Bones break up and joints slip out of place | Warmth and swelling; the shape may start to change | Fractures, bone fragments, dislocations |
| 2 (coalescence) | Healing begins and fragments start to fuse | Less warmth and swelling | Early healing |
| 3 (reconstruction) | The bones are stable again, in whatever shape they healed | No warmth; any change in shape is now fixed | Healed bone, often with a lasting deformity |
The stages are named after Sidney Eichenholtz, who described stages 1 to 3 in 1966; stage 0 was added in 1990. For you, a simpler split matters more: active (warm, swollen, still changing) or in remission (settled). Treatment is about protecting the foot’s shape until it gets from one to the other, and in studies the IWGDF reviewed, people caught at stage 0 and immobilized right away rarely went on to develop a deformity.
Treatment: protect the shape while the inflammation burns out
There is no pill for Charcot. Treatment is mechanical: hold the foot and ankle still and take weight off them until the inflammation settles, so the bones heal in a shape you can still walk on.
- A total contact cast is the first choice. It is a carefully padded cast molded to the leg from the toes to just below the knee, which spreads pressure evenly and can’t be taken off. The IWGDF recommends a non-removable knee-high device: a total contact cast first, a knee-high walking boot made non-removable second, and a removable knee-high boot worn at all times only when neither of those is possible.
- Expect frequent cast changes. The ADA and podiatry task force suggests replacing the first cast after about three days, then checking it weekly. Swelling falls quickly in the first weeks, and a cast that has become loose can rub. Visits can usually be spaced out later.
- Take weight off the foot. Crutches, a walker, a knee scooter or a wheelchair are usually needed. Guidelines differ on how strict to be: the ADA says a suspected Charcot foot needs total non-weight-bearing and urgent referral, NICE advises no weight on it until specialist treatment starts, and the IWGDF accepts some weight through a knee-high cast or boot if you use walking aids. Until a specialist tells you otherwise, keep your weight off it completely, but don’t hop on the other foot: it is often numb too, and a fall or the extra strain can injure it.
- Not a surgical shoe or sandal. Devices that stop below the ankle don’t hold the bones still enough, and the IWGDF advises against them for active Charcot.
How long? Months, not weeks. Treatment continues until the swelling has gone, the temperature of the affected foot has come down close to the other one, and X-rays or an MRI show the bones healing. The IWGDF says swelling alone isn’t a good enough guide, and its experts keep the foot protected for another four to six weeks after the signs settle. In a UK audit, the median time to settle was nine months for people treated in a non-removable cast or boot and 12 months for the rest. A removable boot is tempting, and it costs time.
Why there is no pill
Because Charcot involves runaway bone breakdown, researchers have tried osteoporosis drugs and steroids to calm it. None has earned a place. The 2023 IWGDF guideline says not to use alendronate, pamidronate, zoledronate, calcitonin, parathyroid hormone or methylprednisolone for active Charcot, and suggests not using denosumab. In the UK audit, people who were given bisphosphonates took longer to settle, not shorter, though a comparison like that can’t prove the drug was to blame. What the IWGDF does suggest is checking whether you need vitamin D and calcium while the bones heal.
This is a research-funding problem as much as a medical one. Charcot is uncommon, the drug trials have been small, and the IWGDF’s own list of unanswered questions is long. Rare conditions struggle to attract the money that large trials need. Until someone funds them, the cast is the treatment.
Our take. If you have neuropathy, treat a warm, swollen foot as Charcot until it has been ruled out, even if it barely hurts and even if the X-ray is normal. Get your weight off it that day, not after the MRI. Months in a cast is a hard sell for a foot that doesn’t hurt, and plenty of people talk themselves into a removable boot or ordinary shoes. Don’t. The shape your foot heals in is the shape you will walk on for the rest of your life.
When surgery is needed
Many Charcot feet are managed without surgery, but in specialist-center studies four to five in 10 needed an operation of some kind. The IWGDF suggests considering it when the foot or ankle is unstable, when the deformity is likely to cause an ulcer even inside a cast or boot, or when pain can’t be controlled in a cast. Surgeons also operate for bony bumps that shoes or braces can’t accommodate, ulcers that won’t heal, and infection in the bone. Options include:
- Removing a bony prominence (an exostectomy) that keeps breaking down the skin of the sole.
- Lengthening the Achilles tendon or calf muscle, which takes some of the force off the middle of the foot.
- Reconstruction: realigning and fusing the collapsed joints with plates, screws, rods or an external frame. It is major surgery with a long recovery. In a 2020 review of 1,116 reconstructed feet, 86% fused, 36% had a complication, 5.5% ended in amputation and 91% were walking again, though these were carefully selected patients.
- Amputation, as a last resort, when infection or instability can’t be controlled.
Surgeons generally prefer to let the inflammation settle first when they can. Treatment without surgery often fails for Charcot of the ankle, and for severe ankle Charcot the task force says surgery could be considered as a first-line treatment.
After the cast: protecting the foot for life
Remission isn’t a cure, which is why the IWGDF uses that word instead of “healed.” Go straight from the cast to ordinary shoes and normal walking, and the process can reactivate, with new fractures. The bones are also often thin after months of immobilization.
- Step down gradually, often through a Charcot restraint orthotic walker (CROW), a custom-molded knee-high boot, or a custom brace, before moving to shoes. Build up walking slowly.
- Wear footwear made for the foot you now have, such as extra-depth shoes with custom insoles or fully custom shoes, for life. The IWGDF makes this a strong recommendation. Choosing shoes for diabetic feet.
- Keep up lifelong checks with a foot specialist, usually every three to six months, or every one to three months if you have ever had a foot ulcer or an amputation or have kidney failure, including a temperature comparison, and look at both feet every day. The daily foot check.
- Look after the other foot. It carries extra load while you are in a cast. Wear a supportive shoe on it and report any warmth, swelling or sore straight away.
- Stop smoking. In the Swiss clinic, smokers were more likely to develop ulcers and to need amputations.
Done well, the outlook is better than most people fear. In the Swiss clinic, 93% of feet that were first treated without surgery were still free of a major amputation a median of about five years later, though about four in 10 needed some kind of operation along the way, and three in four people could still walk six blocks without a cane or walker. But Charcot came back in 14% of feet, and ulcers were common. Once an ulcer forms on a Charcot deformity, the risk of a major amputation climbs six- to 12-fold, the IWGDF says.
Charcot is also a sign of how much diabetes has affected the body as a whole. In a large US veterans study, 28% of people with Charcot died within five years, compared with 19% of people with diabetes alone. That is a reason to give your heart, kidneys and blood sugar the same attention as your foot. Can you die from neuropathy?
Can you catch it early at home?
Possibly, and it is worth knowing how. Because a hot spot is the first sign, some foot clinics coach people at high risk to check their foot temperatures at home with an inexpensive infrared thermometer. The IWGDF’s ulcer-prevention guideline suggests that people at moderate or high risk check once a day, and treats a difference of more than 2.2°C (4°F) between the same spots on the two feet, two days in a row, as the signal to cut back walking and see a clinician. That advice was written to prevent ulcers. One small trial that also counted Charcot found two cases among people getting usual care and none among those checking temperatures at home, far too few to show whether home checks catch Charcot sooner. But the warning sign is the same: a foot that runs hotter than its partner. A thermometer can’t rule Charcot out, though, so if a foot looks swollen or red, don’t wait for a second reading: keep your weight off it and get it seen urgently.
When to get help
See a foot specialist urgently, ideally within a day or two, if you have neuropathy and one foot or ankle becomes warm, swollen or red, even if it doesn’t hurt, or if its shape changes. If you can’t get a specialist appointment that fast, see your primary care clinician or an urgent care clinic the same day and ask them to arrange an urgent referral. The ADA says unexplained swelling, redness or warmth of the foot should be referred urgently, and NICE says within one working day. Keep all your weight off the foot until you are seen.
Get same-day or emergency care if there is also an open wound, pus, red streaks spreading up the leg, fever or chills, or if your calf is swollen and painful or you are short of breath, which can mean a blood clot.
Common questions
Is Charcot foot painful?
Often much less than you would expect, and sometimes not at all, because of the neuropathy. Some people do have significant pain. How much it hurts tells you little about how much damage is happening, so don’t use pain as your guide.
How long does Charcot foot take to heal?
The active phase usually takes many months. In a UK audit, the median was nine months for people treated in a cast or non-removable boot and 12 months for the rest. After that comes a gradual step-down to a brace or custom shoes, and protective footwear for life.
Can you walk on a Charcot foot?
Not normally while it is active. Until you have been seen, keep your weight off it completely. After that, any walking should be in a knee-high cast or boot, with crutches, a walker or a knee scooter taking most of your weight, as your specialist directs.
Can Charcot foot be reversed?
The inflammation can settle and the bones can heal, but a deformity that has already formed usually stays unless it is corrected surgically. That is why early immobilization matters: people caught at the earliest stage and treated right away rarely develop a deformity.
Is Charcot foot the same as Charcot-Marie-Tooth disease?
No. Both carry the name of the same French neurologist, Jean-Martin Charcot, but Charcot-Marie-Tooth disease is an inherited neuropathy, while Charcot foot is a bone and joint complication of neuropathy. The numbness of Charcot-Marie-Tooth disease can occasionally lead to a Charcot foot. Charcot-Marie-Tooth disease.
Does Charcot foot lead to amputation?
Usually not, if it is treated well. In a Swiss clinic, 93% of feet that were first treated without surgery were still free of a major amputation about five years later. The risk rises sharply once an ulcer forms on the changed foot, which is why custom footwear and daily foot checks matter for life.
Related reading
Diabetic neuropathy · The daily foot check · Best shoes for diabetics · The monofilament test · Autonomic neuropathy · Can you die from neuropathy?
Sources and further reading: Wukich DK et al. (International Working Group on the Diabetic Foot), Guidelines on the diagnosis and treatment of active Charcot neuro-osteoarthropathy in persons with diabetes mellitus (IWGDF 2023), Diabetes/Metabolism Research and Reviews, 2024; Rogers LC et al., The Charcot foot in diabetes, Diabetes Care, 2011; American Diabetes Association, Retinopathy, neuropathy, and foot care: Standards of Care in Diabetes—2026; NICE, Diabetic foot problems: prevention and management (NG19); StatPearls, Charcot neuropathic osteoarthropathy; American Academy of Orthopaedic Surgeons, Diabetic Charcot foot; Game FL et al., Audit of acute Charcot’s disease in the UK: the CDUK study, Diabetologia, 2012; Gratwohl V et al., Long-term follow-up of conservative treatment of Charcot feet, Archives of Orthopaedic and Trauma Surgery, 2022; Rosenbaum AJ, DiPreta JA, Classifications in brief: Eichenholtz classification of Charcot arthropathy, Clinical Orthopaedics and Related Research, 2015; Ha J et al., Charcot foot reconstruction outcomes: a systematic review, Journal of Clinical Orthopaedics and Trauma, 2020; Pinzur MS, Benchmark analysis of diabetic patients with neuropathic (Charcot) foot deformity, Foot & Ankle International, 1999; Pinzur M, Surgical versus accommodative treatment for Charcot arthropathy of the midfoot, Foot & Ankle International, 2004; Lavery LA et al., Home monitoring of foot skin temperatures to prevent ulceration, Diabetes Care, 2004; Sohn MW et al., Mortality risk of Charcot arthropathy compared with that of diabetic foot ulcer and diabetes alone, Diabetes Care, 2009; Bus SA et al. (IWGDF), Guidelines on the prevention of foot ulcers in persons with diabetes (IWGDF 2023); Merck Manual Professional Version, Neuropathic arthropathy.
This page is general education and is not a diagnosis, a treatment plan, or a substitute for care from your own clinician. Clinical review by Dr. Biernacki is pending; the review date will be shown here once complete.
For our Michigan neighbors
A warm, swollen foot
and numb feet?
Dr. Biernacki’s Michigan practice treats Charcot foot at every stage, from total contact casting while it is active to custom bracing and footwear once it settles, and reconstruction when a foot has become unstable. If you have neuropathy and a newly warm, swollen foot, ask for an urgent appointment and keep your weight off it until you are seen.
Everywhere else, take this page to your own clinician.

Dr. Tom Biernacki, DPM, FACFAS is a double board-certified foot and ankle surgeon (ABFAS and ABPM) and a Fellow of the American College of Foot & Ankle Surgeons. He is the founder of Balance Foot & Ankle in Howell and Bloomfield Township, Michigan, where peripheral neuropathy, diabetic foot risk and loss of protective sensation are part of his weekly clinic. His patient education videos have drawn more than 950,000 subscribers on YouTube. Managing Neuropathy is written by its editorial team under his direction, to put the explanation he gives in the exam room in front of the people who cannot get to one — including when a product is worth buying and when it is not.